
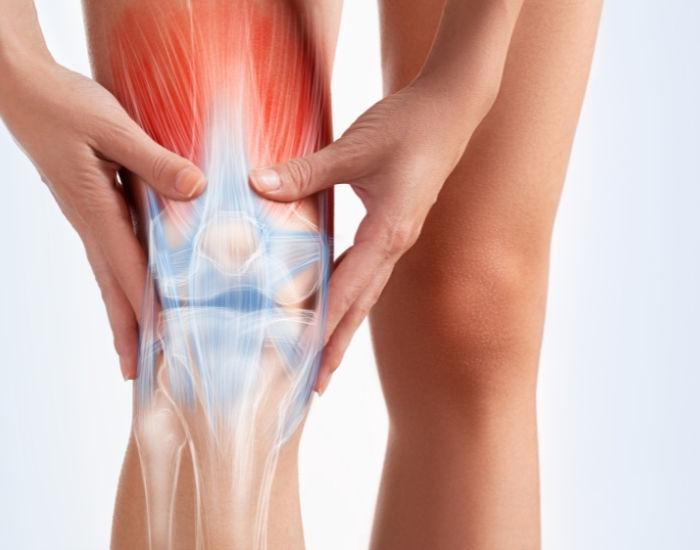
Knee osteoarthritis, often called wear-and-tear arthritis, occurs when the cartilage in your knee joint deteriorates over time. Arthritis of the knee can affect people of all ages, though it’s more common as you get older. The risk factors for developing knee arthritis include:
- Age: The risk of knee arthritis increases with age. It’s more common in people over 50, but it can develop earlier due to certain conditions or injuries.
- Gender: Women are more likely to develop arthritis of the knee compared to men, particularly osteoarthritis.
- Obesity: Excess weight puts additional stress on the knee joints, increasing the risk of arthritis.
- Previous Injury: Injuries to the knee, such as fractures or ligament tears, can increase the likelihood of developing arthritis later in life.
- Genetics: Family history plays a role. If you have close relatives with arthritis, you may be at a higher risk.
- Occupation and Activities: Jobs or activities that involve repetitive stress on the knees, such as heavy lifting or kneeling, may increase the risk.
- Other Medical Conditions: Certain medical conditions, such as rheumatoid arthritis, gout, or metabolic disorders, can predispose someone to developing knee arthritis.
- Joint Alignment: Abnormalities in joint alignment can contribute to uneven wear and tear on the knee joint, leading to arthritis.

Quick Answer: Arthritis of the knee joint, most often osteoarthritis, is a gradual breakdown of the cartilage that cushions the ends of the thigh and shin bones, together with inflammation of the joint lining and changes in the bone underneath. It causes pain with activity, stiffness after rest, swelling and grinding. Treatment usually starts with exercise, weight management, physical therapy and medication, then injections. For persistent pain in people who are not ready for or not suited to knee replacement, genicular artery embolization (GAE) is a minimally invasive option.
It’s important to note that while these factors can increase the risk of developing arthritis, they don’t guarantee it. Additionally, some people with none of these risk factors may still develop knee arthritis, while others with several risk factors may never develop it.
Knee arthritis can lead to a range of symptoms, including:
- Pain: Persistent pain in the knee joint, particularly with movement or weight-bearing activities.
- Stiffness: Difficulty in moving the knee, especially after periods of inactivity, like sitting or sleeping.
- Swelling: Swelling around the knee joint, caused by inflammation as the body reacts to the breakdown of cartilage.
- Decreased range of motion: Difficulty fully bending or straightening the knee.
- Grinding or crunching sensation: Often described as a feeling of grinding, popping, or crunching within the knee joint during movement.
- Weakness or instability: Feeling of instability or giving way in the knee, making it difficult to support weight or perform daily activities.
- Bony growths: Formation of bone spurs (osteophytes) around the edges of the joint, visible on X-rays.
- Deformity: In advanced cases, the knee joint may become visibly deformed or misaligned.
If you’re experiencing these symptoms, it’s essential to consult a healthcare professional for an accurate diagnosis and appropriate management. Treatment options may include medication, physical therapy, lifestyle modifications, genicular artery embolization or in severe cases, knee joint replacement. At Premier vein and vascular center, we offer a new revolutionary treatment for arthritis of knee, called “genicular artery embolization” or GAE. This new treatment provides immediate pain relief, improves range of movement and better quality of life. contact us today to learn more about GAE and how it can help alleviate your knee pain!

Meet your vein specialist
Dr. Syed Raza, MD
Vascular & Interventional Radiology · Founder, Premier Vein & Vascular Center
Fellowship-trained interventional radiologist, board certified in diagnostic and interventional radiology with a Certificate of Added Qualification (CAQ) in interventional radiology, and a Fellow of the Royal College of Radiologists (UK). Member of SIR and RSNA. Former Chief of Interventional Radiology at UTMB Galveston and Memorial Hermann Memorial City, with 15+ years treating varicose veins, venous reflux and peripheral arterial disease.
What Happens Inside a Knee With Arthritis
The knee is a hinge joint where the thigh bone (femur), shin bone (tibia) and kneecap (patella) meet. The ends of these bones are covered with smooth articular cartilage, and two rubbery C-shaped pads called menisci sit between them. A thin lining, the synovium, produces fluid that lubricates the joint. In a healthy knee, these structures let the bones glide almost without friction.
In knee osteoarthritis, the cartilage gradually thins, roughens and develops cracks. The bone underneath reacts by thickening and forming bone spurs at the joint edges. The synovium becomes inflamed, producing extra fluid and swelling. Over time, the joint space narrows, which is what doctors see on an X-ray.
Why arthritic knees hurt
Cartilage itself has no nerves, so pain does not come from the cartilage wearing away directly. It comes from the structures around it: the inflamed synovium, the stressed bone beneath the cartilage, the joint capsule and surrounding ligaments. Research has also shown that inflamed knees develop extra small blood vessels in the lining, and new nerve fibers tend to grow alongside them. This abnormal blood supply is one reason arthritic knees can ache even at rest, and it is the target of genicular artery embolization.
Types of Knee Arthritis: Osteoarthritis and Other Forms
The original article above focuses on osteoarthritis, which is by far the most common type. Other forms of arthritis can also affect the knee, and the distinction matters because treatment differs.
| Type | What drives it | Typical pattern | Main treatment focus |
|---|---|---|---|
| Osteoarthritis | Cartilage breakdown and joint stress over time | Pain with activity, short morning stiffness, often one or both knees | Exercise, weight loss, therapy, injections, GAE, replacement |
| Rheumatoid arthritis | Autoimmune inflammation of the joint lining | Both knees and small joints of hands and feet, long morning stiffness | Disease-modifying medicines from a rheumatologist |
| Post-traumatic arthritis | Earlier fracture, ligament or meniscus injury | Develops in the previously injured knee, sometimes at a younger age | Similar to osteoarthritis, plus attention to alignment and stability |
| Gout and pseudogout | Crystal deposits in the joint | Sudden attacks of a hot, red, very painful knee | Medications to treat attacks and lower crystal formation |
Genicular artery embolization is studied and used mainly for osteoarthritis. Inflammatory arthritis and gout are usually managed by a rheumatologist first.
How Knee Osteoarthritis Progresses
Knee arthritis usually develops slowly over years, and symptoms do not always match what an X-ray shows. Some people with significant changes on imaging have little pain, while others with mild changes struggle every day. Doctors often grade the X-ray from mild to severe:
- Early: Small bone spurs, little or no narrowing of the joint space. Pain after long walks or sports.
- Moderate: Clear narrowing in part of the joint, more spurs. Pain on stairs, stiffness after sitting, intermittent swelling.
- Advanced: Marked narrowing, bone rubbing on bone in places, possible deformity such as bowing of the leg. Pain with most daily activities and sometimes at night.
Progression is not inevitable or predictable. Strengthening the thigh muscles, managing weight and staying active can keep many knees working well for years.
Living day to day with an arthritic knee
Small adjustments add up. Patients often find that a firmer, higher chair is easier to rise from, that leading with the stronger leg going up stairs and the sore leg going down reduces strain, and that breaking long errands into shorter trips keeps pain under control. A few minutes of gentle movement in the morning, such as straightening and bending the knee while still seated on the bed, can ease early stiffness. Ice after activity helps some people, while heat before activity suits others.
Treatment Options for Arthritis of the Knee Joint
Knee arthritis treatment is usually layered, starting with the simplest measures and adding more as needed. Several approaches are often combined.
Foundation: exercise, weight and activity changes
Strengthening the quadriceps and hip muscles takes load off the knee joint, and low-impact exercise such as cycling, swimming and walking keeps the joint nourished. For people who are overweight, even modest weight loss reduces the force passing through the knee with every step. Physical therapy helps design a program that you can stick with.
Medications and supports
Over-the-counter pain relievers and topical anti-inflammatory gels help many people. Oral anti-inflammatory medicines can be effective but are not safe for everyone, particularly people with kidney disease, stomach ulcers or heart conditions. Braces, shoe inserts and a cane in the opposite hand can also reduce strain.
Injections
Corticosteroid injections can calm a flare for weeks to months. Hyaluronic acid and other injection types are used in some patients, with variable results. Injections tend to become less effective over time in advanced arthritis.
Genicular artery embolization (GAE)
GAE is a minimally invasive procedure performed by an interventional radiologist. Through a tiny puncture, usually at the top of the thigh, a thin catheter is guided under X-ray imaging into the small genicular arteries that supply the knee lining. Microscopic particles are then delivered to reduce the abnormal blood flow in the inflamed areas. The aim is to calm inflammation and the pain signals that come with it. It is done as an outpatient procedure, and most people go home the same day. You can read more on our genicular artery embolization page.
Knee replacement
Total or partial knee replacement remains an effective treatment for advanced arthritis. It is major surgery with a significant recovery period. Some people are not good candidates because of other health conditions, and others prefer to delay surgery as long as possible.
| Option | How invasive | Usual recovery | Often considered for |
|---|---|---|---|
| Exercise and physical therapy | Non-invasive | None; ongoing program | Everyone with knee arthritis |
| Steroid injection | Needle injection | Same day | Flares and short-term relief |
| Genicular artery embolization | Catheter through a small puncture | Usually home the same day; light activity soon after | Mild to moderate osteoarthritis with persistent pain despite conservative care |
| Knee replacement | Major surgery | Weeks to months of rehabilitation | Advanced arthritis with severe pain and loss of function |
Who May Be a Candidate for Genicular Artery Embolization?
GAE is not right for every arthritic knee. It is generally considered for adults who:
- Have knee pain from osteoarthritis that has lasted several months or longer
- Have tried conservative treatments such as exercise, therapy, medication or injections without enough relief
- Are not ready for knee replacement, prefer to delay it, or are not good surgical candidates
- Have pain mainly in one area of the knee that can be pointed to
It is usually not recommended for people with active infection in the knee, inflammatory arthritis that has not been addressed, a recent knee replacement on that side, or severe circulation problems in the leg. Kidney function and allergies to X-ray contrast are also reviewed beforehand.
What to Expect From the GAE Procedure
- Preparation. You arrive at the procedure suite, change into a gown and have an IV placed. Mild sedation helps you relax while staying comfortable.
- Access. The skin at the top of the thigh is numbed and a small tube is placed in the artery through a needle puncture.
- Mapping. Contrast and X-ray imaging show the arteries around the knee. Areas of abnormal blood flow often appear as a blush on the images.
- Embolization. Tiny particles are delivered into the selected small branches to reduce that abnormal flow.
- Recovery. The catheter is removed, pressure or a closure device seals the puncture, and you rest for a few hours before going home.
Temporary skin discoloration over the knee, mild soreness and bruising at the puncture site are among the more common short-term effects. Your team will review the specific risks with you before the procedure. Most people return to light daily activities within a day or two, and physical therapy is often continued afterward, because stronger muscles help protect the knee whatever other treatment is used.
Seek urgent medical care if you notice:
- A hot, red, very swollen knee with fever or chills, which can signal a joint infection
- Sudden calf swelling, pain or warmth, which may be a blood clot
- Inability to bear weight after a fall or twist of the knee
- A cold, pale or numb foot, or heavy bleeding or a growing lump at a procedure puncture site
How We Evaluate Knee Arthritis Pain
- Focused history. We ask where the pain is, what makes it worse, how it affects walking, stairs and sleep, and which treatments you have already tried.
- Examination. We assess swelling, tenderness, range of motion, alignment and stability of the knee, and check the circulation in the leg.
- Imaging review. Weight-bearing X-rays show the stage of arthritis. An MRI may be reviewed or recommended when other problems such as a meniscus tear or bone stress need to be ruled out.
- A clear plan. We explain whether GAE is a reasonable option for you, how it fits with physical therapy and other care, and what results and recovery to expect.
Knee Arthritis Care in Houston
If knee pain is limiting your walking, sleep or work and the usual treatments have not been enough, it may be time to ask whether genicular artery embolization is an option. Dr. Syed Raza is a fellowship-trained interventional radiologist board certified in diagnostic and interventional radiology by the American Board of Radiology and a Fellow of the Royal College of Radiologists (UK), and a former Chief of Interventional Radiology at UTMB Galveston and Memorial Hermann Memorial City. Our Houston vein and vascular clinic offers GAE consultations for patients from across Greater Houston and Katy. Learn more on our knee pain treatment page, or call (832) 321-5355. Most insurance plans, including Medicare, are accepted.
Talk With a Specialist at Premier Vein
Have questions about your symptoms or treatment options? Dr. Syed Raza and the team at Premier Vein & Vascular Center can evaluate your concerns and explain your options clearly. Same-week appointments are usually available, and most insurance plans are accepted.
Frequently Asked Questions
Can knee arthritis be reversed?
Damaged cartilage does not grow back, so osteoarthritis cannot be fully reversed. Pain and function can often improve a great deal with exercise, weight management, therapy and targeted treatments, and progression can be slowed.
Is walking good for arthritis in the knee?
For most people, yes. Regular walking keeps the joint mobile and strengthens the supporting muscles. Start with comfortable distances, wear supportive shoes and consider cycling or swimming on days the knee is sore.
What is the difference between GAE and a knee replacement?
Knee replacement removes the damaged joint surfaces and replaces them with an implant, which requires major surgery and rehabilitation. GAE leaves the joint in place and reduces abnormal blood flow to the inflamed lining through a catheter, with most people going home the same day.
Does genicular artery embolization affect a future knee replacement?
GAE does not remove or alter the joint structures, so it does not rule out knee replacement later. Patients should still discuss timing with both their interventional radiologist and orthopedic surgeon.
How do I know if my knee pain is arthritis?
Arthritis pain usually builds gradually, worsens with activity, and comes with stiffness after rest, swelling and grinding. A physical exam and weight-bearing X-rays confirm the diagnosis and rule out other causes.
Is GAE covered by insurance?
Coverage for genicular artery embolization varies by insurance plan. Our team can check your benefits and explain any requirements before the procedure is scheduled.
ABOUT PREMIER VEIN & VASCULAR CENTER: Premier Vein & Vascular Center, a leading vein clinic in Houston and among the top specialized vein treatment clinics in the USA, has provided expert vein care for over 20 years. The center offers minimally invasive treatments for varicose veins, spider veins, and deep vein thrombosis, led by Dr. Syed Raza, MD, a Board-Certified Vein Specialist and Interventional Radiologist. Dedicated to pain-free, healthier living, the clinic delivers cutting-edge, patient-centered care for optimal results.
Trusted Health Resources
- Osteoarthritis, National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIH)
- Osteoarthritis, Centers for Disease Control and Prevention